

Still in pain despite treatment or surgery?
If back, leg, neck or arm pain still limits your life, get a careful review of your options—including whether spinal cord stimulation is appropriate.
Request an SCS Evaluation (Form)Telehealth or in person. Your request does not confirm an appointment.
Dr. Louis G. Cornacchia III · Neurosurgeon
Implantation, programming and revision

Device selection depends on your individual evaluation.
An evaluation is a next step.
It is not a commitment to an implant.
Persistent pain can have more than one cause. We review your symptoms, imaging and previous treatment before discussing whether SCS, another treatment or further evaluation makes sense.
Review the cause of your pain
Bring available imaging, previous operative reports and a list of treatments you have tried.
Discuss the alternatives
Understand the expected benefits, limitations and risks before choosing your next step.
Consider a temporary trial
A trial can help assess your response before a decision about a permanent system.

Meet Dr. Cornacchia.
Louis G. Cornacchia III, M.D., FAANS, FACS
A board-certified neurosurgeon with 30 years of spinal cord stimulation experience. Your evaluation focuses on your diagnosis, prior care and goals—not on assuming a device is the answer.
Read Dr. Cornacchia’s training and experience →How spinal cord stimulation works
Watch this explanation created by Dr. Cornacchia.
What is placed—and where?
SCS uses implanted leads and a pulse generator to deliver stimulation intended to help manage selected chronic pain conditions.
Lead position, generator location, programming and device choice depend on the patient. SCS does not correct every structural problem or guarantee pain relief.
Educational illustration. Placement varies by patient.
Clear answers. Realistic expectations.
Who may benefit from an evaluation?
Selected patients with persistent pain despite appropriate treatment, including some patients with continuing symptoms after spine surgery. Your pain pattern, diagnosis and previous care determine whether SCS deserves consideration.
Does an evaluation mean I need surgery?
No. Evaluation may lead to nonsurgical care, further diagnostic work, a different procedure or discussion of an SCS trial.
What are the risks and limitations?
Risks can include infection, bleeding, lead movement, device problems, neurological injury and inadequate pain relief. Further procedures may be needed. This is not a complete list; individual risks and alternatives require a clinical discussion.
What should I bring?
Available MRI or CT images and reports, prior operative reports, device information if applicable, medication details and your treatment history.
Full SCS evaluation, treatment pathway, research and FAQs
COORDINATED SCS CARE
One Coordinated Team—from Your SCS Trial to Long-Term Care.
Dr. Cornacchia works closely with experienced pain-management physicians throughout your treatment. Your pain-management doctor may perform the initial trial, while Dr. Cornacchia performs the permanent implantation.
A shared treatment plan
Your pain-management physician and neurosurgeon coordinate the trial, implant decision, and follow-up.
Preserve the leads when appropriate
When clinically appropriate, our techniques allow the trial leads to remain in place for connection to the permanent generator—avoiding a second lead-placement procedure.
Support as your needs change
If your system later needs reprogramming, generator replacement, or surgical evaluation, your neurosurgeon and pain-management physician work together to help you get the best possible benefit from your stimulator.
Is spinal cord stimulation the right next step for your pain?
SCS is considered for selected patients with persistent neuropathic pain when a careful workup suggests that stimulation may help function and pain control, and when other causes that need different treatment have been addressed.
Problems that may prompt an SCS evaluation
- Persistent pain after spine surgery. Burning, shooting, or radiating nerve pain that continues after a back operation.
- Chronic back or leg pain. Pain that continues despite appropriate nonsurgical care, when further surgery is not appropriate.
- Painful diabetic neuropathy. Persistent burning or painful feet and legs from diabetic nerve damage despite appropriate treatment.
- Complex regional pain syndrome (CRPS). Severe limb pain and sensitivity that need specialist assessment.
What SCS does — and does not do
SCS is designed to modulate pain signaling. It does not fix structural compression, progressive weakness, spinal instability, infection, tumor, fracture, or diabetes itself.
If imaging, neurologic examination, or symptoms suggest a problem that needs decompression, stabilization, medical treatment, or urgent evaluation, that issue comes first.
A trial-first pathway with modern programming options.
Modern SCS systems may use different stimulation patterns, including approaches with or without a tingling sensation. Evaluation focuses on diagnosis, realistic goals, trial response, programming and follow-up.
See the device. See where it goes.
What the implanted device looks like
The pulse generator contains the battery and electronics. Thin leads connect it to the stimulation electrodes. These are examples of available devices, not a recommendation for a particular model.
Device image: Medtronic. View device information.
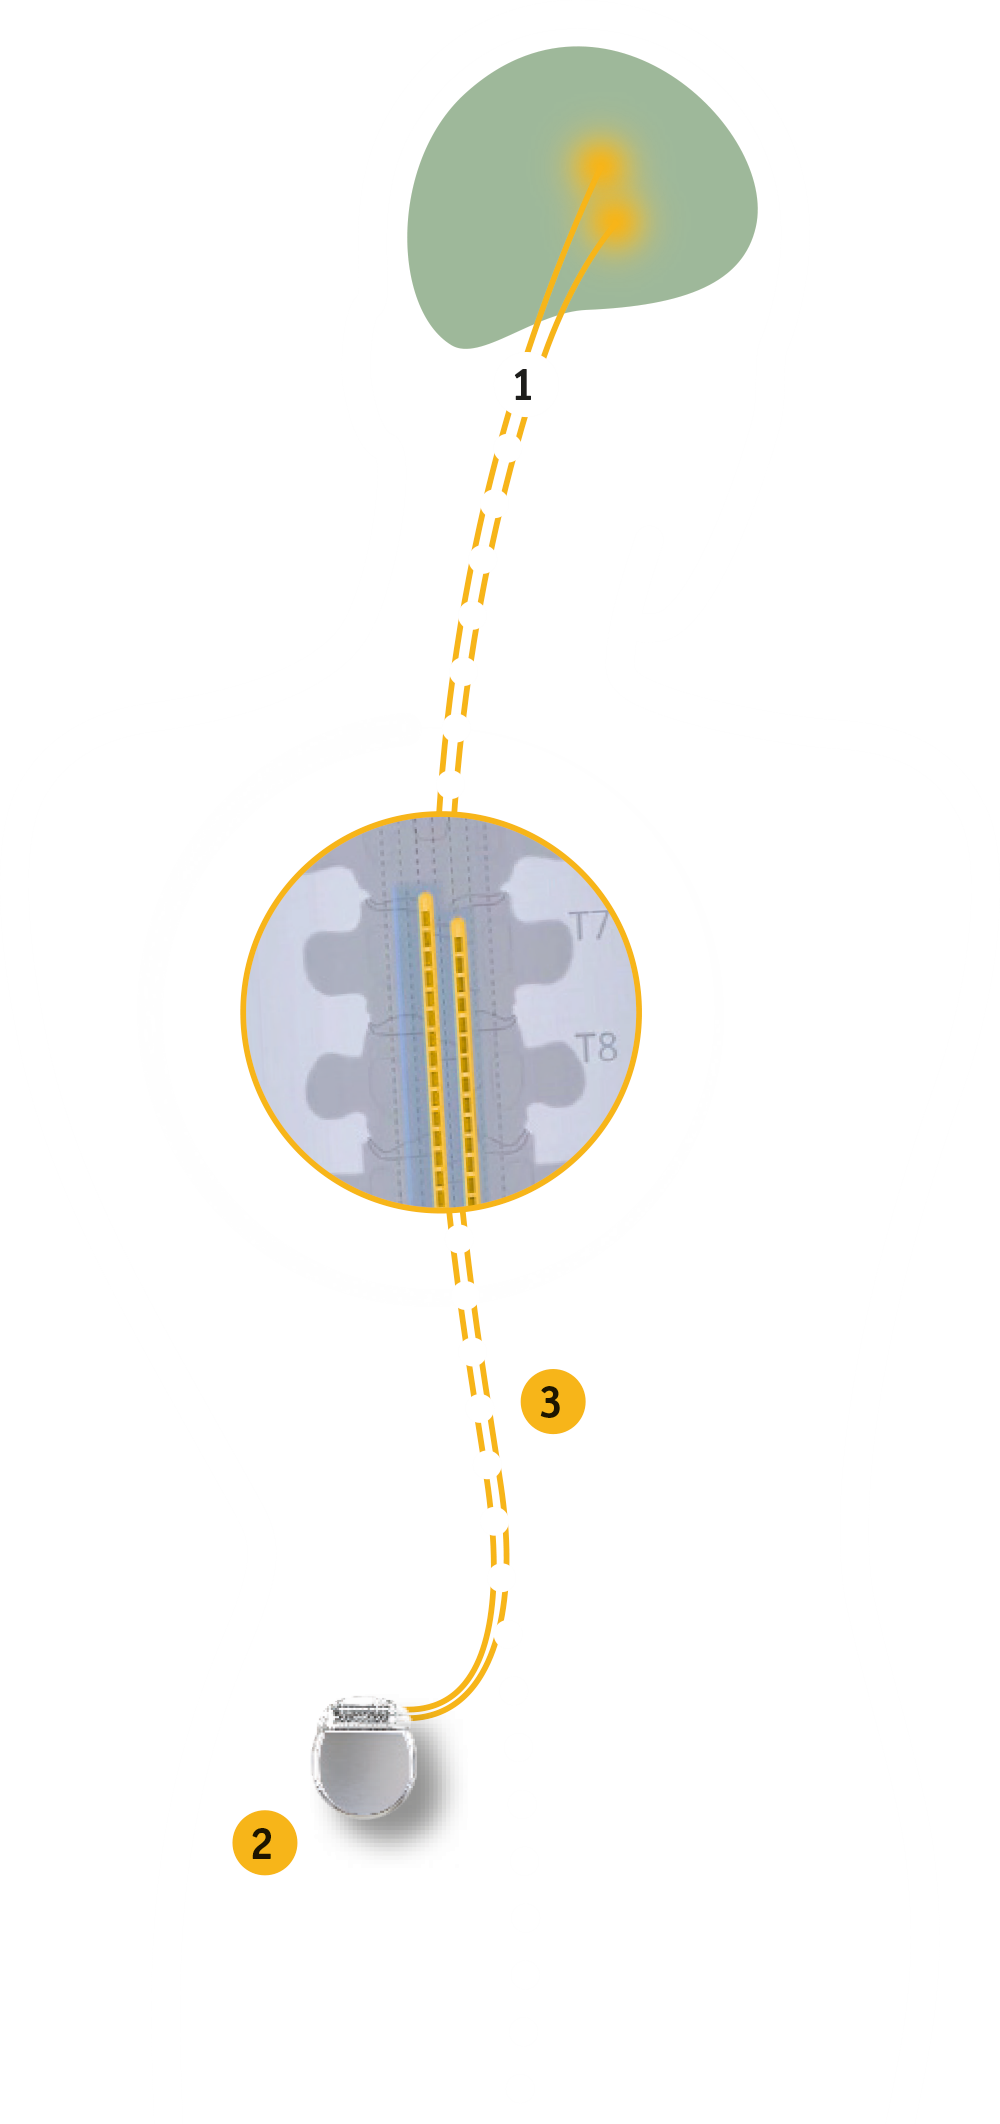
Typical implantation sites
Leads: placed in the epidural space along the spinal cord. The illustration shows a mid-back location for treating lower-body pain.
Pulse generator: placed in a pocket beneath the skin; the example shows the upper buttock/hip area. The connecting wires are also beneath the skin.
Your lead level and generator site are chosen for your pain pattern, anatomy, comfort and device. This illustration is not a surgical placement guide.
Illustration: Boston Scientific. View manufacturer explanation.
Your SCS treatment pathway
A decision at each stage. A shared plan throughout.
- 1
Find the pain generators
Assess symptoms, examination, imaging and prior treatment. Identify causes that can be addressed directly before considering SCS.
- 2
Neurosurgical evaluation
Check for compression, instability or another structural problem needing specific treatment. Determine whether SCS is appropriate.
- 3
Pain-management evaluation
Review medications, rehabilitation and prior procedures. Complete any needed screening and agree on pain and activity goals.
- 4
Temporary stimulation trial
Test stimulation and measure meaningful improvement in pain and daily function before considering a permanent implant.
- 5
Implant, test and program
If the trial supports proceeding, implant the system. Perform intraoperative checks and testing suited to the device and anesthesia, then individualize programming.
- 6
Postoperative care
Check healing, review precautions and device use, adjust programming and coordinate medication management. Monitor pain relief and function over time.
If the implanted system provides no benefit
Reassess the diagnosis, device and programming. If there is still no meaningful benefit, discuss removal of the implanted leads and pulse generator with your treating team. Removal requires a planned clinical procedure.
Lead management depends on the trial technique. Temporary percutaneous trial leads are usually removed. With a planned staged approach, suitable implanted trial leads may remain in place for connection to the permanent generator when clinically appropriate. Your neurosurgeon and pain-management physician tailor the sequence, testing and follow-up to your needs.
Ready to discuss whether SCS fits your diagnosis?
Request an evaluation so Apteum can review your symptoms, records, goals and prior treatment history.
What published studies can — and cannot — tell you.
Research can help frame the discussion, but study results are not a prediction of your individual outcome. Your diagnosis, prior treatment, neurologic findings, anatomy, device selection, programming and trial response matter.
These studies examined different patients, devices and definitions of success. Their percentages cannot be compared directly. Some were industry funded. Study results are not Apteum patient outcomes, and individual results vary.
View detailed published response rates, chart and citations
PUBLISHED RESPONSE RATES BY CONDITION
What does “success” mean? Most pain-response studies use at least 50% pain relief. The diabetic-neuropathy and CRPS studies below use different measures, which are labeled on each result.
Nonsurgical refractory back pain: 2022 trial
At 3 months, 80.9% of patients receiving 10 kHz SCS achieved at least 50% pain relief, versus 1.3% receiving conventional medical management alone. Participants had no prior spine surgery and a spine-surgeon assessment confirming they were not surgical candidates.
PROCESS trial, 2007
In selected patients with neuropathic leg pain after prior back surgery, 48% of patients assigned to SCS plus conventional medical management achieved at least 50% leg-pain relief at 6 months, compared with 9% assigned to conventional medical management alone.
DTM trial, 2021
In a randomized trial of selected patients with chronic back and leg pain, 83.7% receiving differential target multiplexed stimulation achieved at least 50% back-pain relief at 12 months, compared with 51.1% receiving traditional SCS.
SENZA-PDN trial, 2021
In selected patients with painful diabetic neuropathy, 79% receiving 10 kHz SCS plus conventional medical management met a composite endpoint of at least 50% pain relief without neurological deterioration at 3 months, compared with 5% receiving conventional medical management alone.
CRPS type I: Kemler trial, 2000
At 6 months, 39% of patients assigned to SCS plus physical therapy rated themselves “much improved,” compared with 6% assigned to physical therapy alone. This is a patient-rated overall improvement measure, not a 50% pain-relief responder rate.
Benefit can diminish: the overall groups were similar at five years.
Modern advances: nearly twice the profound-relief response in one trial
In the same 2021 DTM study, 69% of DTM patients versus 35% of traditional SCS patients achieved at least 80% back-pain relief at 12 months. This result describes one treatment, one study population, and a specific pain-relief threshold; it is not a prediction of your outcome.
Read the DTM study behind this comparison
These studies examined different patients, devices, and definitions of success. Their percentages cannot be compared directly. Some were industry funded. Study results are not Apteum patient outcomes, and individual results vary.
Experienced neurosurgical judgment before device decisions.
A spinal cord stimulator is a medical device decision, but it is also a diagnosis decision. Apteum’s evaluation is designed to clarify whether SCS is reasonable, whether another spine problem needs attention, and what goals should define success for you.
Louis G. Cornacchia III, MD
Dr. Cornacchia is a neurosurgeon with 30 years of experience placing spinal cord stimulators. He works with a community of experienced pain-management doctors and with Medtronic, Boston Scientific, and other manufacturers.
Manufacturer relationships do not imply endorsement of a specific device for every patient. Brand and system selection should be based on clinical need, anatomy, MRI considerations, programming goals, prior device history, and shared decision-making.

 Additional systems as clinically appropriate
Request a telehealth or in-person SCS evaluation.
If pain is still controlling your life after surgery, nonsurgical care, neuropathy treatment, or an existing stimulator problem, Apteum can help you understand whether spinal cord stimulation deserves consideration.
Prepare for your visit
For the most useful evaluation, bring or upload prior procedure history, recent imaging reports or discs, a medication list, and the make/model information for any existing stimulator.
Our team will contact you to discuss your request and arrange the next step. Your request does not confirm an appointment.
Contact
Spinal Cord Stimulation FAQ
Who may be a candidate for spinal cord stimulation?
Why is there a trial before a permanent implant?
Can I get an MRI with a spinal cord stimulator?
What if I already have a stimulator and it is not working well?
What are the risks?
Does SCS treat diabetes, compression, weakness, or instability?
Find out whether SCS fits your situation.
Request a telehealth or in-person evaluation to review your pain, previous treatment and options.
The team will contact you to discuss your request. No outcome is guaranteed.